



ICU Management & Practice, Volume 26 – Issue 3, 2026
 PRINT OPTIMISED
SCREEN OPTIMISED
Artificial intelligence (AI) is increasingly used across the transplant continuum to improve organ utilisation, clinical decision-making, and personalised care. However, its adoption must address unique ethical challenges related to scarce resources, vulnerable patients, and public trust. This review emphasises trustworthiness as the foundation for AI implementation, introducing the GRAFT Checklist to assess AI systems across their clinical lifecycle. Integrated with the Understand–Transform–Sustain (UTS) framework, it supports the ethical, transparent, and accountable use of AI in transplantation.
Introduction
Advances in artificial intelligence (AI) and machine learning (ML) have enabled increasingly sophisticated approaches to clinical prediction, diagnostic support, workflow optimisation, and decision-making across healthcare (Obermeyer and Emanuel 2016). In transplant medicine, growing availability of large clinical datasets, national transplant registries, electronic health records (EHR), medical imaging repositories, and advances in computational modelling have accelerated development of AI technologies (Arjmandmazidi et al. 2025; Vivek and Papalois 2025). Applications now extend across the entire transplant continuum, from donor screening to post-transplant care (Arimandmazidi et al. 2025; Olawade et al. 2025), with potential to improve clinical efficiency and support individualised treatment (Olawade et al. 2025). However, the growing influence of AI also raises important questions regarding the appropriate role of algorithmic systems in a field characterised by uncertainty, complexity, and profound ethical significance (Gawlikowski et al. 2023).
Several features distinguish transplantation from other clinical domains, including a national waitlist exceeding 160,000 candidates and at least 13 deaths each day while awaiting transplantation (Hart et al. 2024; UNOS 2025). This context of persistent organ scarcity requires difficult decisions regarding the allocation of life-saving resources. High-stakes clinical judgment directly affects access to treatment for critically sick patients, graft function, and patient survival. Transplantation also depends on complex stakeholder workflows spanning organ procurement organisation (OPO) coordinators, physicians, surgeons, pathologists, social workers, pharmacists, amongst many other professionals. Consequently, public trust is fundamental to the integrity of organ donation and allocation systems. The introduction of AI into this setting therefore carries substantial clinical, ethical, and societal implications.
The growing integration of AI into transplantation raises a fundamental question: when should an AI system be trusted? Despite the rapid technical progress, there is no transplant-specific framework to address this question. Traditional evaluations of AI models frequently emphasise performance metrics such as accuracy, discrimination, and calibration. However, these measures do not determine whether an AI system should be relied upon in clinical practice. Algorithms may demonstrate excellent predictive performance while remaining opaque, difficult to interpret, vulnerable to bias, or inadequately validated across diverse patient populations (Guidotti et al. 2018). Furthermore, uncertainty remains an inherent characteristic of ML systems, particularly when models are deployed in environments that differ from their training conditions (Gawlikowski et al. 2023). Clinicians may hesitate to adopt recommendations from black-box models (Guidotti et al. 2018), while patients and families may question decisions lacking adequate transparency or human oversight (Amann et al. 2020). More broadly, public confidence in organ donation could be undermined if AI-driven processes are perceived as inequitable. Evaluating AI in transplantation requires moving beyond technical metrics toward a broader set of principles, emphasised by international organisations and emerging AI governance frameworks (WHO 2021).
Previous studies have summarised emerging applications of AI across the transplant continuum (Arjmandmazidi et al. 2025; Vivek and Papalois 2025; Olawade et al. 2025), indicating its immense promise. Comparatively limited attention has been devoted to developing transplantation-specific frameworks for responsible AI adoption (Kourounis et al. 2026). Therefore, the aim of this critical review is to give a brief overview of current uses of AI in the field, assess its associated ethical challenges and propose a transplantation-specific framework, shifting the discussion from “what AI can do” to “when and why AI should be trusted”.
Part I: Applications of AI Across the Transplant Continuum
1. Donor Identification and Donor Management
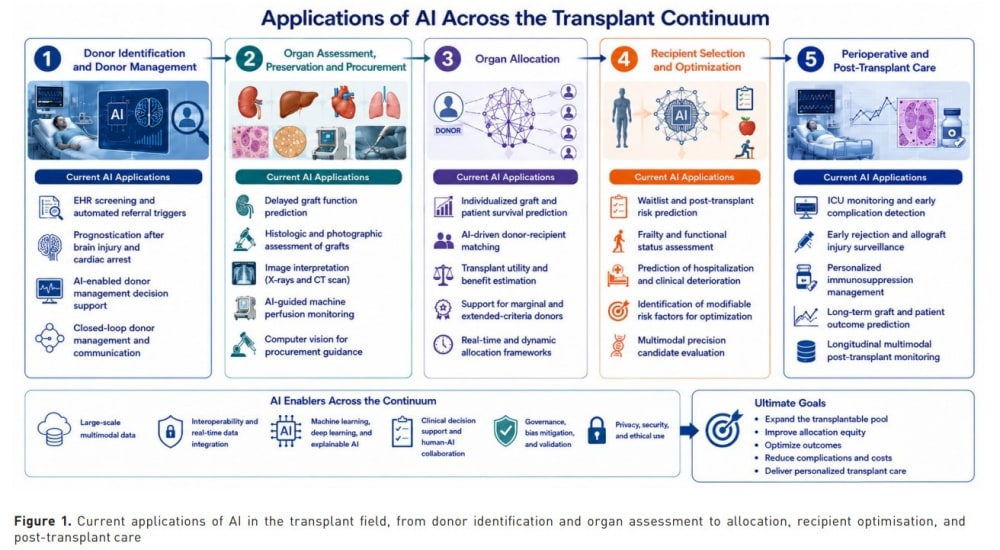
In the intensive care unit (ICU), AI-based EHR donor screening has been demonstrated in retrospective studies and can potentially identify organ donors and predict donor eligibility (Sauthier et al.2023) (Figure 1). Additionally, the use of automated referral triggers in single-centre evaluations has been reported to increase donors by up to 92%, though high false-positive rates risk straining ICU workflows and creating OPO over-reliance on algorithms (Levan et al. 2022). Beyond donor identification, AI has been explored for prognostication after catastrophic brain injury and cardiac arrest, using explainable AI models that process post-resuscitation head CT scans and quantitative EEG reactivity that predict mortality and progression to brain death (Kawai et al. 2023; Amorim et al. 2019). This may aid clinicians and OPOs in coordinating timely authorisation, withdrawal of life-sustaining treatment (WLST), and procurement, potentially improving organ utilisation. To assist donor management and optimise organ quality, AI-enabled clinical decision-support systems can integrate longitudinal EHR data with real-time haemodynamic measurements, medication administration records, and ventilator parameters to support individualised management (Yoon et al. 2022; Keddie 2025). This may be especially useful in complex cases like donation after circulatory death (DCD). Centralised donor-care workflows, including dedicated Donor Care Units (DCUs) (Croome et al. 2026), also provide a potential future setting for integrating AI-enabled decision support, documentation, donor assessment, and workflow-coordination tools.
2. Organ Assessment, Preservation and Procurement
Standardising donor organ quality assessment is critical to reducing subjectivity and expanding the transplantable pool (Arjmandmazidi et al. 2025; Al Moussawy et al. 2024 (Figure 1). In kidney transplantation, ML models have predicted delayed graft function using donor and recipient characteristics, histopathology, procurement-related variables, hypothermic machine-perfusion parameters, and long-term kidney outcomes (Li et al. 2024; Tirasattayapitak et al. 2024; Klein et al. 2023). In liver assessment, deep-learning analysis of donor-biopsy histology and ML assessment of procurement photographs can quantify graft steatosis compared with visual assessment alone (Piella et al. 2024; Kourounis et al. 2026). For donor hearts, ML models incorporating donor clinical and imaging diagnostic variables, including left-ventricular ejection fraction and hypertrophy, have predicted organ acceptance, while CT-based ML has been evaluated for donor-lung screening (Wayda et al. 2024; Ma et al. 2025; Ram et al. 2023). During ex vivo perfusion, AI applications integrate real-time metabolic and haemodynamic monitoring across machine perfusion systems (Sage et al. 2023). By utilising continuous perfusate trends, AI-based machine perfusion analysis may allow for individualised graft management and improve viability (Sage et al. 2023; van Leeuwen et al. 2024; Bikramaditya et al. 2025; Dong et al. 2026). In another case, AI has integrated donor clinical, laboratory, histopathologic, and transcriptomic data and identified that some rejected livers had molecular profiles like accepted grafts, exposing potential transplant suitability among discarded organs (Srivastava et al. 2024). Finally, emerging computer-vision and workflow-recognition systems can analyse operative video and robotic kinematic data to identify surgical phases, instruments, actions, and anatomical structures, supporting intraoperative guidance and spatial localisation. Although these technologies have not yet been validated specifically for deceased-donor organ procurement, they could potentially be adapted for these practices (Olawade et al. 2025; Knudsen et al. 2024; King et al. 2025).
3. Organ Allocation
Current organ allocation systems such as the Model for End-Stage Liver Disease (MELD), Lung Composite Allocation Score (Lung-CAS), and Kidney Allocation System (KAS) have improved the standardisation of organ distribution and waitlist prioritisation (Kamath et al. 2001; Egan et al. 2006; Israni et al. 2014). However, these systems include predefined variables and weighting schemes that may not capture the multifactorial determinants of post-transplant outcomes (Bertsimas et al. 2019; Ayllón et al. 2018). AI and ML models can and have thus emerged as promising tools to support organ allocation decisions (Figure 1). These models can simultaneously analyse large numbers of donor, recipient, immunologic, and peri-transplant variables to generate individualised predictions of graft and patient survival (Bertsimas et al. 2019; Mark et al. 2019; Ravindhran et al. 2023). More recently, advanced AI-based allocation models have been applied to predict expected benefit of individualised donor-recipient matching and aim to identify pairings associated with improved outcomes beyond survival prediction (Ayllón et al. 2018; Pruinelli et al. 2025; Alowidi et al. 2024; Firuzpour et al. 2025). These models may also support the decisions regarding choice of machine perfusion with marginal or extended-criteria donor organs that might otherwise be discarded (Sage et al. 2023). Future applications may enable real-time matching with dynamic updating of outcome predictions as each patient’s clinical condition evolves and new longitudinal data becomes available.
4. Recipient Selection and Optimisation
AI can be applied for candidate evaluation and risk stratification throughout the transplant process (Al Moussawy et al. 2024) (Figure 1). ML models have been developed to predict waitlist mortality, post-transplant survival, graft failure, and perioperative complications using large clinical datasets like Standard Transplant Analysis and Research (STAR) (Bertsimas et al. 2019; Mark et al. 2019; Pruinelli et al. 2025). For example, Bertsimas et al’s (2019) ML model improved prediction of 3-month waitlist mortality and, in simulated liver-allocation analyses, was projected to prevent approximately 418 annual waitlist deaths compared with MELD-based allocation. In addition, these models can support centre-level candidate selection by identifying patients most likely to benefit from transplantation and estimating expected post-transplant outcomes (Bertsmias et al. 2019; Ayllón et al. 2018). AI has also been applied to frailty assessment and functional status evaluation (McAdams-DeMarco et al. 2015; Oliosi et al. 2022), which may facilitate individualised recipient optimisation by identifying modifiable risk factors and guiding targeted interventions. For example, Malamutmann et al’s (2025) AI-based body composition score utilising CT images to quantify muscle and fat volumes in liver-transplant recipients was able to associate visceral fat-to-muscle ratio with post-transplant survival, therefore identifying patients who could benefit from targeted nutritional support and individualised exercise prehabilitation (Quint et al. 2023). Predictive models have further been used to identify those patients at risk for hospitalisation, clinical deterioration, and increased healthcare utilisation while awaiting transplantation (Bertsimas et al. 2019; Berchuck et al. 2024). Future applications may enable increasingly individualised approaches to candidate selection and peri-transplant care.
5. Perioperative and Post-Transplant Care
Following transplantation, AI and ML models have been applied to postoperative monitoring and risk stratification in the ICU (Ding et al. 2025) (Figure 1). These approaches have been used to identify haemodynamic instability, predict postoperative complications, and detect early graft dysfunction or clinical deterioration before conventional recognition (Michard et al. 2025; Komorowski et al. 2018). As patients progress beyond the immediate postoperative period, AI has increasingly been explored for allograft surveillance and early detection of rejection. By integrating imaging, biomarkers, histopathology, digital pathology, and multi-omics data, these models may improve the identification of acute and chronic allograft injury (Ravindhran et al. 2023; Gotlieb et al. 2022; Halloran et al. 2014). Similar approaches have been applied to immunosuppression management, where predictive models may support personalised dosing strategies, estimate rejection risk, and anticipate drug-related toxicities (Hoffert et al. 2024; Waillard et al. 2021; Waillard et al. 2017). Beyond the early post-transplant phase, AI has been investigated for long-term graft surveillance and outcome prediction, including graft survival, patient survival, readmissions, and medication adherence (Gotlieb et al. 2022). Future applications may enable increasingly individualised monitoring and management strategies throughout long-term transplant follow-up.
Part II: Ethical Challenges Regarding AI in Transplant
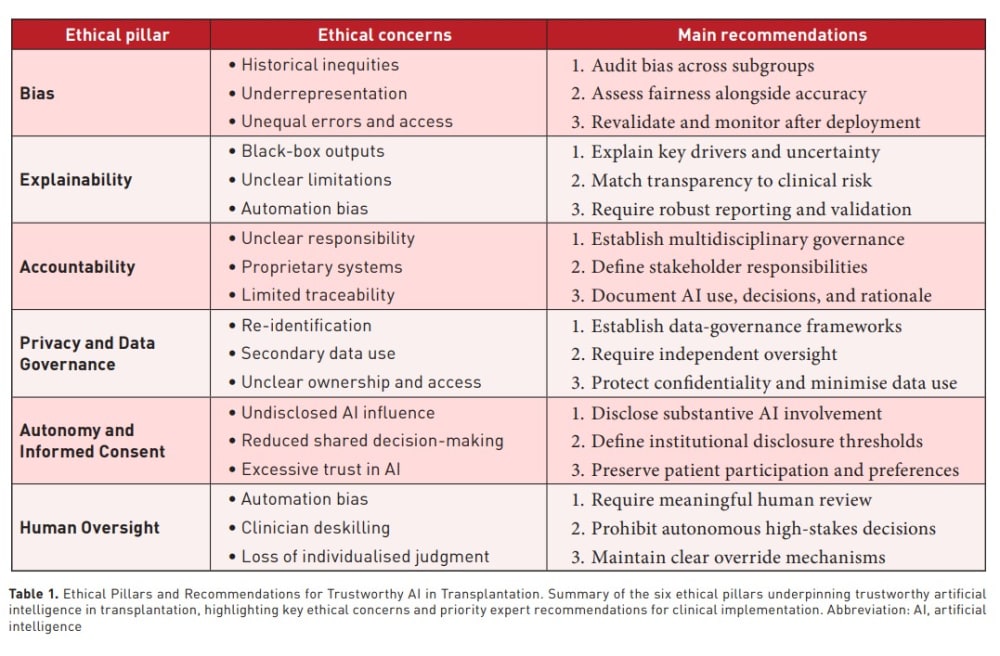
Despite promising results, most AI applications across the transplant continuum remain in early stages of validation and have not yet demonstrated consistent improvements in real-world patient-centred outcomes. Nevertheless, as these technologies become integrated into routine clinical practice, questions of trust become as important as questions of performance. The successful adoption of these innovations will depend not only on their ability to improve clinical decision-making, but also on whether their recommendations are perceived as fair, transparent, reliable, and ethically justified to physicians, patients, caregivers, and the public. Trust in AI can be conceptualised as the justified willingness of stakeholders to rely on algorithm-informed recommendations under conditions of uncertainty. Such trust depends on multiple ethical principles that determine whether an AI system deserves to influence clinical care. The following sections examine six pillars that underpin trustworthy AI in transplantation: bias, explainability, accountability, privacy, autonomy, and human oversight.
1. Bias - Is it Fair?
Because transplantation allocates scarce, life-saving organs, even modest algorithmic differences across patient groups can alter listing, prioritisation, and survival opportunities (Drezaa-Kleiminger et al. 2023; Salybekov et al. 2025). AI models may reproduce inequities already embedded in their training datasets, including differences associated with racial minorities, socioeconomic position, insurance coverage, geography, and access to transplant centres (Wesselman et al. 2021; Ding et al. 2022). These variables are not neutral: they often reflect historical practices, structural barriers, and unequal opportunities to reach evaluation or transplantation rather than biologic differences alone (Chen et al. 2023; Wesselman et al. 2021). Consequently, models for candidate selection, waitlist mortality, transplant benefit and donor-recipient matching may convert prior disparities into apparently objective predictions (Drezaa-Kleiminger et al. 2023; Salybekov et al. 2025; Chen et al. 2023). A highly accurate model can therefore remain ethically unacceptable if errors or adverse recommendations are concentrated among historically underserved groups (Chen et al. 2023). Efficiency gains may even worsen equity when algorithms preferentially optimise outcomes toward the populations best represented in training data (Salybekov et al. 2025: Chen et al. 2023). For example, Ding et al. (2022) reported how a liver graft-failure model performed well overall but showed substantial racial disparities because the largest racial group dominated the training data.
Position statement: Before and during AI implementation, responsible organisations should conduct bias audits, report calibration, discrimination, and error rates across clinically and socially relevant subgroups, and evaluate whether model use impacts waitlisting, organ-offer acceptance, access or outcomes (Salybekov et al. 2025; Chen et al. 2023; Gerbaud et al. 2026). Fairness can be operationalised using predefined metrics such as subgroup calibration, equalised odds, or differences in prediction of error rates, each reflecting different ethical priorities (Chen et al. 2023). Model performance should undergo external validation and periodic reassessment as patient populations, allocation policies, and clinical practices evolve over time (Salybekov et al. 2025; Chen et al. 2023; Gerbaud et al. 2026). Several iterative Plan-Do-Study-Act (PDSA) cycles may be required to refine interventions and ensure equitable model performance after deployment (Gerbaud et al. 2026). Finally, transplant programmes should recognise that fairness constraints may reduce overall predictive performance, requiring explicit value-based decisions regarding the appropriate balance between equity and aggregate utility.
2. Explainability: Can We Understand It?
Explainability of an AI model is essential, but even more so when it informs decisions that must be justified to patients, families, transplant teams, OPOs, and oversight bodies (Drezaa-Kleiminger et al. 2023; Assis de Souza et al. 2025). In transplantation, recommendations concerning allocation priority, rejection risk, or listing and delisting can have irreversible consequences, making an unexplainable output difficult to evaluate or take into consideration (Drezaa-Kleiminger et al. 2023; Salybekov et al. 2025). Explainability may take different forms, including global explainability (e.g. how a model generates predictions overall) and local explainability (e.g. why a specific prediction was generated), both of which may be necessary to support transplant decision-making. This challenge is greatest with complex neural networks and proprietary systems whose internal logic, training data, or performance limitations may be inaccessible to clinicians or underreported by its creators (Assis de Souza et al. 2025; Zhang and Zhang 2023). Poorly designed explanations, whether unintentionally or deliberately, may also promote automation bias, leading clinicians to accept erroneous recommendations or disregard conflicting clinical information (Khera et al. 2023; Jabbour et al. 2023).
Position statement: Health systems must demand explainability from developers and vendors when considering adopting their models. A clinically useful explanation should identify the variables most responsible for a given recommendation, their direction of influence, relevant uncertainty, and circumstances in which the model may be unreliable (Assis de Souza et al. 2025; Zhang and Zhang 2023; Amann et al. 2022). Such explanations should also be readily interpretable during routine clinical workflows. Additionally, explainability requirements should be tailored to the clinical context and potential consequences of error; high-risk applications must be met by equally high levels of transparency, traceability, and robust validation (Assis de Souza et al. 2025; Zhang and Zhang 2023; Amann et al. 2022). For clinical prediction models, adherence to the TRIPOD+AI reporting guideline can help address transparency gaps by requiring complete reporting of the data, model-development methods, performance evaluation, intended use, and limitations (Collins et al. 2024).
3. Accountability - Who is Responsible?
Accountability becomes complex when AI influences transplant decisions, since an algorithm cannot be summoned to the bedside, or the courtroom. When a recommendation must become a decision, the clinician who calls the shots retains the immediate professional responsibility (Zhang and Zhang 2023; Lawton et al. 2024; Mello et al. 2024). Harm may occur when an advisory system contributes to an incorrect allocation recommendation, missed rejection signal, or inappropriate listing or delisting (Salybekov et al. 2025; Lawton et al. 2024). The responsibility behind these recommendations may be attributed to many different stakeholders, including developers, vendors, hospitals, clinicians, surgeons, OPOs, and regulators (Zhang and Zhang 2023). This creates uncertainty about who did and who did not have the knowledge, authority, or ability to prevent an error (Zhang and Zhang 2023; Lawton et al. 2024; Mello and Guha 2024). Assigning all responsibility to the bedside clinician is problematic when a model is proprietary, inadequately validated, poorly implemented, or difficult to challenge; clinicians may become “liability sinks” for failures originating elsewhere (Lawton et al. 2024). Recognising these challenges, regulatory frameworks such as those from the U.S. Food and Drug Administration (FDA) increasingly emphasise lifecycle accountability, requiring ongoing oversight through premarket evaluation, post-deployment monitoring, and continuous performance assessment of AI systems (FDA 2021). AI should not displace professional judgment or justify decisions that cannot otherwise be clinically and ethically defended (Zhang and Zhang 2023; Mello and Guha 2024).
Position statement: Before deployment, institutions should establish multidisciplinary governance by defining model ownership, approval criteria, human oversight, monitoring responsibilities, and procedures for suspension or withdrawal if necessary (Loufek et al. 2024). Accountability should be distributed across the AI lifecycle, with developers responsible for model design, institutions for independent validation and governance, clinicians for appropriate implementation and professional judgment, and regulators for establishing oversight and performance standards (Loufek et al. 2024; Federal Register 2024; FDA 2025; FDA 2026). We propose that each institution’s health record document when AI was used, its recommendation, the human decision, and reasons for overriding or following the output, preserving traceability of actions taken and accountability (Zhang and Zhang 2023; Loufek et al. 2024).
4. Privacy and Data Governance: How is Patient Data Being Used?
The development of AI systems depends on access to large, high-quality datasets, making data governance a central ethical consideration in transplantation. Unlike many other areas of medicine, this field generates highly sensitive longitudinal information that may follow donors and recipients for years or even decades (Price and Cohen 2019; Marley et al. 2020). AI models are increasingly trained using data derived from transplant registries, including Organ Procurement and Transplantation Network (OPTN)/United Network for Organ Sharing (UNOS) and Scientific Registry of Transplant Recipients (SRTR), OPO records, multicentre collaborations, EHRs, and molecular and pathology records (Gotlieb et al. 2022). While these data sources create opportunities for innovation, they also introduce important ethical challenges regarding privacy and governance. The aggregation of large datasets increases the risk of patient re-identification, even when information has been de-identified prior to analysis. For instance, Rocher et al. estimated that 99.98% of individuals in a de-identified U.S. dataset could be uniquely re-identified using generative modelling with as few as 15 demographic variables (Rocher et al. 2019). Questions also arise regarding the secondary use of data, cross-institutional data sharing, commercial access to patient information, and the ownership of data used to develop AI systems (Mittelstadt et al. 2016). For example, the transfer of 1.6 million NHS patient records to Google's DeepMind for AI development sparked international debate regarding secondary data use, informed consent, and commercial access to healthcare data (Powles and Hodson 2017). The transplant field creates distinct privacy challenges given the unique structure of data registries which link donor characteristics-recipient outcomes, lifelong follow-up information, and genomic data. International collaborations further complicate governance by introducing differences in regulatory standards, data protection requirements, and oversight mechanisms (Vayena et al. 2018).
Position Statement: We believe that transplant AI systems should not be developed or deployed without clearly defined governance frameworks that regulate data access, sharing, and secondary use. Independent oversight should be required when longitudinal and linked donor-recipient datasets are used. AI development should adhere to data minimisation principles whenever feasible and prioritise the protection of donor and recipient confidentiality. Although the transplant field has historically upheld rigorous data stewardship practices, AI may present new challenges due to the quantity of data needed for development. For this, we reinforce that transparency and accountability continue to be considered prerequisites at the forefront of AI implementation.
5. Autonomy and Informed Consent: Do Patients Know and Participate?
Respect for patient autonomy is a foundational principle of biomedical ethics and requires that patients remain meaningful participants in decisions affecting their care (Childress 2019). Important questions emerge regarding informed consent, shared decision-making, and the extent to which patients should be informed when AI contributes to clinical recommendations (Marley et al. 2020; Char et al. 2018). Bertsimas et al. (2019) developed ML models using OPTN data that outperformed MELD in predicting waitlist mortality among liver transplant candidates and proposed their use to support allocation order3. As similar models become incorporated into centre-based clinical practice, patients may be affected by algorithm-generated recommendations regarding transplant candidacy or prognosis without fully understanding their limitations. In addition, AI system outputs may sway physician and patient decisions regarding acceptance or decline of donor grafts, particularly marginal or extended-criteria organs (Grote and Berens 2020). This influence may occur both through clinician-mediated recommendations and through patients’ independent use of LLMs or other AI tools, whose outputs may be perceived as objective, personalised, or authoritative when interpreting the risks and benefits of an organ offer (Grote and Berens 2020).
Position Statement: We believe that patients should be informed whenever AI systems play a role in high-stakes transplant decisions, including candidacy, waitlist prioritisation, or prognostic assessments. While disclosure of every AI-assisted calculation is neither practical nor necessary, transplant centres should establish clear policies defining thresholds for disclosure, particularly when AI materially alters risk estimates, changes clinical decision pathways, or meaningfully influences high-stakes transplant decisions (Rose and Shapiro 2024; Mello et al. 2025). AI outputs should be integrated into shared decision-making, where clinicians contextualise algorithm-informed recommendations alongside patient values, preferences, and clinical circumstances. Patients should retain the ability to question, contextualise, and ultimately participate in decisions that affect their transplant journey.
6. Human Oversight: Who Remains in Control?
Although AI systems can support increasingly complex transplant decisions, they cannot fully account for patient values, institutional priorities, or the contextual factors that often shape clinical judgment. Human oversight therefore remains essential throughout the transplant continuum. Current models of oversight range from human-in-the-loop systems, in which clinicians actively review and approve recommendations, to human-on-the-loop and human-over-the-loop approaches, where AI assumes a progressively larger role in decision-making (Cabitza et al. 2017; Floridi et al. 2018). For example, Halloran and colleagues (2016) developed the Molecular Microscope Diagnostic System, a machine learning–based platform for rejection assessment in transplant recipients. As such systems increasingly influence rejection diagnosis and immunosuppressive management, questions arise regarding how clinicians should respond when algorithmic interpretations conflict with clinical judgment or conventional diagnostic findings. These tensions also highlight other risks associated with diminished human oversight, as excessive reliance on algorithmic outputs may contribute to automation bias and the gradual deskilling of clinicians (Cabitza et al. 2017; Parasuraman and Manzey 2010).
Position Statement: We believe that AI systems should not be granted autonomous authority to list or delist candidates, allocate organs, accept or decline organ offers, determine treatment plans or interpret imaging and pathology results. Transplant centres should require meaningful human review of AI-assisted recommendations and establish clear mechanisms for overriding algorithmic outputs when clinical judgment or patient-specific circumstances warrant. Human oversight should also serve as a safeguard against model drift, unforeseen errors, and changes in clinical practice that may affect AI performance over time. The degree of human oversight should be proportional to the stakes of the decision, with the highest levels of oversight reserved for decisions that directly affect access to transplantation or patient outcomes. Effective human oversight will also require clinicians to be appropriately trained to critically evaluate and integrate AI-generated recommendations while preserving independent clinical judgment.
Part III: Practical Approach for Trustworthy AI in Transplantation
The ethical challenges discussed throughout this manuscript ultimately converge on a common question: under what conditions should AI systems be trusted in transplantation? Stakeholders in the transplant continuum need practical methods to evaluate whether a given AI system is trustworthy. While the ethical pillars described above identify key areas of concern, they do not by themselves provide a model for implementation. To address this gap, we propose the GRAFT Checklist, a transplant-specific operational evaluation tool that translates ethical principles into actionable criteria for evaluating AI systems before and during clinical deployment (Figure 2).
G - Graft and organ stewardship
AI systems should improve organ stewardship by reducing avoidable organ discard and supporting appropriate organ utilisation. Assessment should include predefined metrics such as organ discard rates, costs, graft survival, and alignment with accepted clinical standards.
R - Reproducible Clinical Performance
AI systems should be externally validated and demonstrate consistent performance across different transplant centres, patient populations, and clinical settings. Evaluation should include external validation across transplant centres, assessment of subgroup calibration, and monitoring performance drift over time.
A - Allocation Justice
AI systems should promote equitable access to transplantation without introducing or amplifying disparities. Evaluation should include fairness of metrics, including subgroup calibration, parity in prediction of error rates, and impact on access to transplantation.
F – Family, Caregivers, and Public Trust
AI systems’ role must be explainable and justifiable to donor families, recipients and the public. Assessment should include transparency measures, public reporting practices, and stakeholder engagement strategies.
T - Traceable Human Oversight
AI systems must preserve meaningful human decision-making authority and allow recommendations to be reviewed, challenged, and overridden when appropriate. Evaluation should include documentation of AI recommendations, clinician responses, override rates, and auditability within the electronic health record.

The GRAFT Checklist is intended for use by transplant programmes, hospital AI oversight committees, quality improvement teams, and regulatory stakeholders. Each GRAFT domain is accompanied by operational criteria that can be assessed qualitatively or quantitatively, allowing stakeholders to determine whether an AI system satisfies predefined thresholds for ethical and operational readiness before implementation. Of note, the family domain includes the multidimensionality of patient-family-healthcare dynamics at its core. It is imperative for AI-enabled donor identification or management to never reduce the donor to a source of organs or displace comfort-focused care, final goodbyes, and respectful end-of-life practices. Likewise, recipients require fair, transparent, and reviewable decisions.
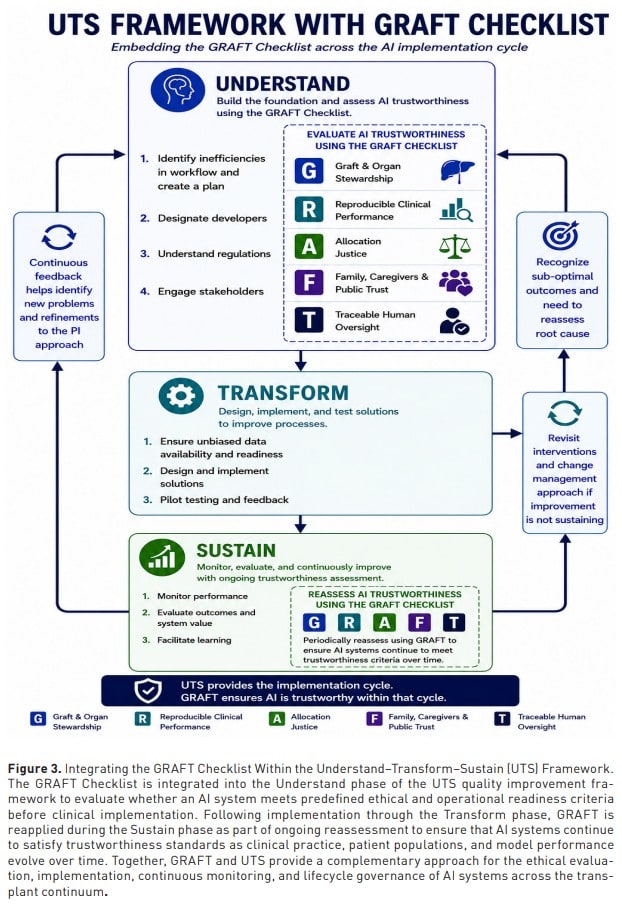
Once an AI system satisfies the principles outlined by GRAFT, successful deployment requires a structured process for integration into clinical workflows. One potential approach is the Understand–Transform–Sustain (UTS) framework (Gerbaud et al. 2026), recently developed at Mayo Clinic as a quality improvement methodology for the responsible implementation of AI and automation in healthcare. UTS accommodates both internally developed and vendor-based tools while emphasising stakeholder engagement, transparency, and patient safety across its three phases. It is also well suited to incorporate simulation-based testing of high-stakes processes to assess adequacy (Croome et al. 2026).
Within this model, GRAFT functions primarily during the Understand phase to evaluate whether an AI system is ethically and operationally ready for adoption before implementation. It may also be reapplied during the Sustain phase as part of periodic reassessment to ensure that AI systems continue to meet trustworthiness criteria over time. UTS then provides the infrastructure for implementation, monitoring, and continuous improvement. Together, these frameworks offer a pathway for translating trustworthy AI principles into real-world transplant practice (Figure 3).
Although GRAFT provides a structured approach for evaluating trustworthiness, it is not intended to function as a prescriptive regulatory standard or replace institutional judgment. The relative importance of individual domains and acceptable implementation of thresholds may vary according to the intended clinical application, institutional resources, regulatory requirements, and local transplant practices. Prospective evaluation and real-world implementation across diverse transplant programmes will be important to refine its operational use and establish its impact on AI adoption. Nevertheless, to our knowledge, GRAFT represents the first transplant-specific operational approach for systematically evaluating the ethical and clinical readiness of AI systems before and throughout implementation.
Conclusion
AI has the potential to improve care across every stage of transplantation. However, strong predictive performance alone does not make an AI system trustworthy. Responsible entities must ensure that these tools protect equity, patient autonomy, privacy, and public trust. Human judgment must remain central to every high-stakes decision, with clear accountability and the ability to override unsafe recommendations. Together, GRAFT and UTS provide a practical pathway to evaluate AI readiness and support its responsible implementation in clinical practice. The future of AI in transplantation will depend not on how quickly it is adopted, but on how responsibly it is governed.
Conflict of Interest
None.
References:
Al Moussawy M, Lakkis ZS, Ansari ZA, et al. The transformative potential of artificial intelligence in solid organ transplantation. Front Transplant. 2024;3:1361491.
Alowidi N, Ali R, Sadaqah M, et al. Advancing kidney transplantation: a machine learning approach to enhance donor-recipient matching. Diagnostics. 2024;14(19):2119.
Amann J, Blasimme A, Vayena E, et al. Explainability for artificial intelligence in healthcare: a multidisciplinary perspective. BMC Med Inform Decis Mak. 2020;20(1):310.
Amann J, Vetter D, Blomberg SN, et al. To explain or not to explain?—Artificial intelligence explainability in clinical decision support systems. PLOS Digit Health. 2022;1(2):e0000016.
Amorim E, van der Stoel M, Nagaraj SB, et al. Quantitative EEG reactivity and machine learning for prognostication in hypoxic-ischemic brain injury. Clin Neurophysiol. 2019;130(10):1908-1916.
Arjmandmazidi S, Heidari HR, Ghasemnejad T, et al. An in-depth overview of artificial intelligence (AI) tool utilization across diverse phases of organ transplantation. J Transl Med. 2025;23(1):678.
Artificial Intelligence/Machine Learning (AI/ML)-Based Software as a Medical Device (SaMD) Action Plan. 2021.
Assis de Souza A, Stubbs AP, Hesselink DA, et al. Cherry on top or real need? A review of explainable machine learning in kidney transplantation. Transplantation. 2025;109(1):123-132.
Ayllón MD, Ciria R, Cruz-Ramírez M, et al. Validation of artificial neural networks as a methodology for donor-recipient matching for liver transplantation. Liver Transpl. 2018;24(2):192-203.
Berchuck SI, Bhavsar N, Schappe T, et al. Use of predictive models to determine transplant eligibility. Curr Transplant Rep. 2024;11(4):243-250.
Bertsimas D, Kung J, Trichakis N, et al. Development and validation of an optimized prediction of mortality for candidates awaiting liver transplantation. Am J Transplant. 2019;19(4):1109-1118.
Bikramaditya M, Ruchu K, Harsha Vardhan R, et al. Artificial intelligence-guided perfusion metrics to predict delayed graft function in deceased-donor kidney transplantation. Kidneys. 2025;14(4):346-355.
Cabitza F, Rasoini R, Gensini GF. Unintended consequences of machine learning in medicine. JAMA. 2017;318(6):517-518.
Char DS, Shah NH, Magnus D. Implementing machine learning in health care—addressing ethical challenges. N Engl J Med. 2018;378(11):981-983.
Chen RJ, Wang JJ, Williamson DFK, et al. Algorithmic fairness in artificial intelligence for medicine and healthcare. Nat Biomed Eng. 2023;7(6):719-742.
Childress JF, Beauchamp TL. Principles of Biomedical Ethics. Oxford University Press; 2019.
Collins GS, Moons KGM, Dhiman P, et al. TRIPOD+AI statement: updated guidance for reporting clinical prediction models that use regression or machine learning methods. BMJ. 2024;385:e078378.
Croome KP, Taner CB, Markuson H, et al. Centralization is the solution to standardization: donation after circulatory death organ recovery at a hospital-based donor care unit. Am J Transplant. 2026;26(5):937-943.
Ding S, Tang R, Zha D, et al. Fairly predicting graft failure in liver transplant for organ assigning. AMIA Annu Symp Proc. 2022;2022:415-424.
Ding Z, Zhang L, Zhang Y, et al. A supervised explainable machine learning model for perioperative neurocognitive disorder in liver-transplantation patients and external validation on the Medical Information Mart for Intensive Care IV database: retrospective study. J Med Internet Res. 2025;27:e55046.
Dong B, Zhao Y, Li Y, et al. Association between hypothermic machine perfusion parameters and graft function in deceased donor kidney transplantation. Ann Med. 2026;58(1):2634488.
Drezga-Kleiminger M, Demaree-Cotton J, Koplin J, et al. Should AI allocate livers for transplant? Public attitudes and ethical considerations. BMC Med Ethics. 2023;24(1):102.
Egan TM, Murray S, Bustami RT, et al. Development of the new lung allocation system in the United States. Am J Transplant. 2006;6(5):1212-1227.
Firuzpour F, Pasha AA, Oliaei F, et al. Artificial intelligence-driven kidney organ allocation: systematic review of clinical outcome prediction, ethical frameworks, and decision-making algorithms. BMC Nephrol. 2025;26(1):639.
Floridi L, Cowls J, Beltrametti M, et al. AI4People—An ethical framework for a good AI society: opportunities, risks, principles, and recommendations. Minds Mach. 2018;28(4):689-707.
Gawlikowski J, Tassi CRN, Ali M, et al. A survey of uncertainty in deep neural networks. Artif Intell Rev. 2023;56(1):1513-1589.
Gerbaud AF, Berguido de la Guardia M, Booth SC, et al. Process improvement before artificial intelligence and automation: building trust with the Understand-Transform-Sustain framework. Mayo Clin Proc Innov Qual Outcomes. 2026;10(4):100725.
Gotlieb N, Azhie A, Sharma D, et al. The promise of machine learning applications in solid organ transplantation. NPJ Digit Med. 2022;5(1):89.
Grote T, Berens P. On the ethics of algorithmic decision-making in healthcare. J Med Ethics. 2020;46(3):205.
Guidotti R, Monreale A, Ruggieri S, et al. A survey of methods for explaining black box models. ACM Comput Surv. 2018;51(5):Article 93.
Halloran PF, Famulski KS, Reeve J. Molecular assessment of disease states in kidney transplant biopsy samples. Nat Rev Nephrol. 2016;12(9):534-548.
Halloran PF, Reeve JP, Pereira AB, et al. Antibody-mediated rejection, T cell-mediated rejection, and the injury-repair response: new insights from the Genome Canada studies of kidney transplant biopsies. Kidney Int. 2014;85(2):258-264.
Hart A, Schladt DP, Snyder JJ. OPTN/SRTR 2024 Annual Data Report: Overview of US Solid Organ Transplantation. Available from: https://srtr.hrsa.gov/adr/2024/Overview/
Health Data, Technology, and Interoperability: Certification Program Updates, Algorithm Transparency, and Information Sharing. 2024.
Hoffert Y, Dia N, Vanuytsel T, et al. Model-informed precision dosing of tacrolimus: a systematic review of population pharmacokinetic models and a benchmark study of software tools. Clin Pharmacokinet. 2024;63(10):1407-1421.
Israni AK, Salkowski N, Gustafson S, et al. New national allocation policy for deceased donor kidneys in the United States and possible effect on patient outcomes. J Am Soc Nephrol. 2014;25(8):1842-1848.
Jabbour S, Fouhey D, Shepard S, et al. Measuring the impact of AI in the diagnosis of hospitalized patients: a randomized clinical vignette survey study. JAMA. 2023;330(23):2275-2284.
Kamath PS, Wiesner RH, Malinchoc M, et al. A model to predict survival in patients with end-stage liver disease. Hepatology. 2001;33(2):464-470.
Kawai Y, Kogeichi Y, Yamamoto K, et al. Explainable artificial intelligence-based prediction of poor neurological outcome from head computed tomography in the immediate post-resuscitation phase. Sci Rep. 2023;13(1):5759.
Keddie L. Increasing donor management communication efficiencies through data capture, consolidation & visualization tools. In: Advancements in Action Case Studies: The Organ Donation Alliance; 2025.
Khera R, Ross J, Simon M. Automation bias and assistive AI: risk of harm from AI-driven clinical decision support. JAMA. 2023;330(23):2255-2257.
King A, Fowler GE, Macefield RC, et al. Use of artificial intelligence in the analysis of digital videos of invasive surgical procedures: scoping review. BJS Open. 2025;9(4).
Klein A, Loupy A, Stegall M, et al. Qualifying a novel clinical trial endpoint (iBOX) predictive of long-term kidney transplant outcomes. Am J Transplant. 2023;23(10):1496-1506.
Knudsen JE, Ghaffar U, Ma R, et al. Clinical applications of artificial intelligence in robotic surgery. J Robot Surg. 2024;18(1):102.
Komorowski M, Celi LA, Badawi O, et al. The Artificial Intelligence Clinician learns optimal treatment strategies for sepsis in intensive care. Nat Med. 2018;24(11):1716-1720.
Kourounis G, Gilbert S, Knight SR, et al. Shaping the future of AI in organ transplantation: position paper of the European Society for Organ Transplantation. Transpl Int. 2026;39.
Kourounis G, Tingle SJ, Elmahmudi A, et al. A scoping review of the photographic assessment of donor liver steatosis in transplantation using artificial intelligence. Clin Transplant. 2026;40(2):e70433.
Lawton T, Morgan P, Porter Z, et al. Clinicians risk becoming "liability sinks" for artificial intelligence. Future Healthc J. 2024;11(1):100007.
Levan ML, Trahan C, Klitenic SB, et al. Short report: evaluating the effects of automated donor referral technology on deceased donor referrals. Transplant Direct. 2022;8(8):e1330.
Li M, Hu X, Li Y, et al. Development and validation of a novel nomogram model for predicting delayed graft function in deceased donor kidney transplantation based on pre-transplant biopsies. BMC Nephrol. 2024;25(1):138.
Loufek B, Vidal D, McClintock DS, et al. Embedding internal accountability into health care institutions for safe, effective, and ethical implementation of artificial intelligence into medical practice: a Mayo Clinic case study. Mayo Clin Proc Digit Health. 2024;2(4):574-583.
Ma W, Oh I, Luo Y, et al. Developing approaches to incorporate donor-lung computed tomography images into machine learning models to predict severe primary graft dysfunction after lung transplantation. Am J Transplant. 2025;25(6):1339-1349.
Malamutmann E, Roehrborn F, Vershinina K, et al. AI-based body composition score predicts survival after liver transplantation. Langenbecks Arch Surg. 2025;410(1):307.
Mark E, Goldsman D, Gurbaxani B, et al. Using machine learning and an ensemble of methods to predict kidney transplant survival. PLoS One. 2019;14(1):e0209068.
Marketing Submission Recommendations for a Predetermined Change Control Plan for Artificial Intelligence-Enabled Device Software Functions. 2025.
McAdams-DeMarco MA, Law A, King E, et al. Frailty and mortality in kidney transplant recipients. Am J Transplant. 2015;15(1):149-154.
Mello MM, Char D, Xu SH. Ethical obligations to inform patients about use of AI tools. JAMA. 2025;334(9):767-770.
Mello MM, Guha N. Understanding liability risk from using health care artificial intelligence tools. N Engl J Med. 2024;390(3):271-278.
Michard F, Mulder MP, Gonzalez F, et al. AI for the hemodynamic assessment of critically ill and surgical patients: focus on clinical applications. Ann Intensive Care. 2025;15(1):26.
Mittelstadt BD, Floridi L. The ethics of big data: current and foreseeable issues in biomedical contexts. Sci Eng Ethics. 2016;22(2):303-341.
Morley J, Machado CCV, Burr C, et al. The ethics of AI in health care: a mapping review. Soc Sci Med. 2020;260:113172.
Obermeyer Z, Emanuel EJ. Predicting the future—big data, machine learning, and clinical medicine. N Engl J Med. 2016;375(13):1216-1219.
Olawade DB, Marinze S, Qureshi N, et al. The impact of artificial intelligence and machine learning in organ retrieval and transplantation: a comprehensive review. Curr Res Transl Med. 2025;73(2):103493.
Oliosi E, Guede-Fernández F, Londral A. Machine learning approaches for the frailty screening: a narrative review. Int J Environ Res Public Health. 2022;19(14):8825.
Parasuraman R, Manzey DH. Complacency and bias in human use of automation: an attentional integration. Hum Factors. 2010;52(3):381-410.
Piella G, Farré N, Esono D, et al. LiverColor: an artificial intelligence platform for liver graft assessment. Diagnostics. 2024;14(15):1654.
Powles J, Hodson H. Google DeepMind and healthcare in an age of algorithms. Health Technol. 2017;7(4):351-367.
Price WN, Cohen IG. Privacy in the age of medical big data. Nat Med. 2019;25(1):37-43.
Pruinelli L, Balakrishnan K, Ma S, et al. Transforming liver transplant allocation with artificial intelligence and machine learning: a systematic review. BMC Med Inform Decis Mak. 2025;25(1):98.
Quint EE, Ferreira M, van Munster BC, et al. Prehabilitation in adult solid organ transplant candidates. Curr Transplant Rep. 2023;10(2):70-82.
Ram S, Verleden SE, Kumar M, et al. CT-based machine learning for donor lung screening prior to transplantation. medRxiv. 2023.
Ravindhran B, Chandak P, Schafer N, et al. Machine learning models in predicting graft survival in kidney transplantation: meta-analysis. BJS Open. 2023;7(2).
Rocher L, Hendrickx JM, de Montjoye YA. Estimating the success of re-identifications in incomplete datasets using generative models. Nat Commun. 2019;10(1):3069.
Rose SL, Shapiro D. An ethically supported framework for determining patient notification and informed consent practices when using artificial intelligence in health care. Chest. 2024;166(3):572-578.
Sage AT, Donahoe LL, Shamandy AA, et al. A machine-learning approach to human ex vivo lung perfusion predicts transplantation outcomes and promotes organ utilization. Nat Commun. 2023;14(1):4810.
Salybekov AA, Yerkos A, Sedlmayr M, et al. Ethics and algorithms to navigate AI's emerging role in organ transplantation. J Clin Med. 2025;14(8):2775.
Sauthier N, Bouchakri R, Carrier FM, et al. Automated screening of potential organ donors using a temporal machine learning model. Sci Rep. 2023;13(1):8459.
Srivastava A, Manchel A, Waters J, et al. Integrated transcriptomics and histopathology approach identifies a subset of rejected donor livers with potential suitability for transplantation. BMC Genomics. 2024;25(1):437.
Tirasattayapitak S, Ratanatharathorn C, Thotsiri S, et al. Integrating clinical and histopathological data to predict delayed graft function in kidney transplant recipients using machine learning techniques. J Clin Med. 2024;13(24):7502.
United Network for Organ Sharing (UNOS). Waitlist deaths decrease: a shared success by the organ donation and transplant community supported by UNOS. Available from: https://unos.org/news/waitlist-deaths-decrease-a-shared-success-by-the-organ-donation-and-transplant-community-supported-by-unos/
Vayena E, Blasimme A. Health research with big data: time for systemic oversight. J Law Med Ethics. 2018;46(1):119-129.
van Leeuwen LL, Irizar H, Kim-Schluger L, et al. The potential of machine learning to predict early allograft dysfunction after normothermic machine perfusion in liver transplantation. J Hepatol. 2024;81(6):e298-e300.
Vivek K, Papalois V. AI and machine learning in transplantation. Transplantology. 2025;6(3):23.
Wayda B, Weng Y, Zhang S, et al. Prediction of donor heart acceptance for transplant and its clinical implications: results from the Donor Heart Study. Circ Heart Fail. 2024;17(10):e011360.
Wesselman H, Ford CG, Leyva Y, et al. Social determinants of health and race disparities in kidney transplant. Clin J Am Soc Nephrol. 2021;16(2):262-274.
WHO Health Ethics and Governance Group. Ethics and governance of artificial intelligence for health: WHO guidance. Geneva: World Health Organization; 2021.
Woillard JB, de Winter BC, Kamar N, et al. Population pharmacokinetic model and Bayesian estimator for two tacrolimus formulations—twice daily Prograf and once daily Advagraf. Br J Clin Pharmacol. 2011;71(3):391-402.
Woillard JB, Labriffe M, Debord J, et al. Tacrolimus exposure prediction using machine learning. Clin Pharmacol Ther. 2021;110(2):361-369.
Yoon JH, Pinsky MR, Clermont G. Artificial intelligence in critical care medicine. Crit Care. 2022;26(1):75.
Zhang J, Zhang ZM. Ethics and governance of trustworthy medical artificial intelligence. BMC Med Inform Decis Mak. 2023;23(1):7.









