



ICU Management & Practice, Volume 26 - Issue 1, 2026
 PRINT OPTIMISED
SCREEN OPTIMISED
Following CE Mark certification in 2025, the Lifemotion® ECMO system has seen early use across Europe, Latin America, and Africa for ground, intra-hospital, and airborne transports. Portability, battery autonomy, and intuitive design enable safe ECMO beyond the ICU. These cases show mobility becoming a core expectation for ECMO platforms. They illustrate extending advanced support to patients wherever needed.
When the Lifemotion® ECMO system received CE Mark certification under the European Union Medical Device Regulation in January 2025, it entered a market defined by high clinical complexity, conservative adoption patterns, and deeply embedded workflows. Extracorporeal membrane oxygenation (ECMO) remains one of the most demanding therapies in modern medicine, typically concentrated in specialised centres with dedicated infrastructure and highly trained teams.
Yet the delivery of critical care is changing. The regionalisation of services, the expansion of inter-hospital retrieval programmes, and growing expectations for rapid response are reshaping how ECMO is used in practice (Labib et al. 2022; Ozgur et al. 2025). Increasingly, clinicians are evaluating not only how an ECMO system performs within the intensive care unit, but how safely and reliably it functions when patients must be moved, stabilised remotely, or treated across multiple care environments (Labib et al. 2022; Ozgur et al. 2025).
Over the past year, early international clinical experience with the ECMO system developed by China-based Lifemotion Medical Technology has begun to reflect this shift. Publicly shared clinical cases across Europe, Latin America, and Africa suggest that portability, power independence, ease of deployment, and system usability are becoming central considerations in ECMO adoption (Labib et al. 2022; Ozgur et al. 2025; Sams et al. 2022).
While several established ECMO platforms already support mobile use, early clinical experience suggests that expectations around portability, power independence, and ease of deployment are continuing to evolve.
Mobility as a Clinical and Safety Imperative
Historically, ECMO systems have been optimised for static use within the intensive care unit, where power supply, monitoring, and alarm architectures assume a fixed environment and limited patient movement. However, the growth of ECMO retrieval programmes and mobile critical care teams is challenging that model. Increasingly, patients require stabilisation at peripheral hospitals followed by transfer to tertiary centres, often under significant time pressure (Labib et al. 2022; Ozgur et al. 2025).
One of the earliest real-world demonstrations of how these demands are reshaping ECMO use occurred in Spain. At the University Hospital Virgen de la Arrixaca in Murcia, 2 clinicians conducted an inter-hospital patient retrieval using the Lifemotion® ECMO system operating entirely on battery power. The case, completed in April 2025, involved uninterrupted extracorporeal support throughout transport, with the motor, pump, and oxygenator functioning independently of external power sources.

Rather than focusing on technological novelty, clinical teams emphasised operational confidence during movement. Continuous real-time monitoring, clear alarm visibility, and an intuitive user interface supported situational awareness throughout transport, allowing clinicians to focus on patient stability rather than device management. Stable gas exchange and haemodynamic support were maintained despite the absence of fixed infrastructure.
Dr Juan Blanco Morillo, ECLS Care and Perfusion Unit Coordinator at the hospital, highlighted the system’s versatility in transport scenarios. “The Lifemotion® system offered a high degree of flexibility during our patient transport case. Its compact design, intuitive user interface, and ability to operate on battery power supported effective extracorporeal support throughout transport. We see potential for its use not only in the ICU, but also in retrieval and emergency scenarios where mobility is essential.”
The Spanish experience illustrates a broader shift in ECMO practice. As care pathways extend beyond the ICU, systems are increasingly expected to deliver consistent levels of safety, visibility, and control regardless of location. In this context, mobility is no longer an adjunct capability but an integral component of modern extracorporeal life support (Labib et al. 2022; Belda Hofheinz et al. 2024).
Portability Taken to the Extreme in Chile
If ground transport challenges traditional ECMO assumptions, airborne deployment pushes system design to its limits (Belda Hofheinz et al. 2024; Sams et al. 2022). In Chile, the Lifemotion® ECMO system was deployed aboard an air ambulance in collaboration with Redcare Santiago, one of the country’s largest ECMO centres. The partnership has included more than six clinical cases, many involving transport scenarios.

Air medical environments impose severe constraints. Space is limited, access to equipment during flight is restricted, and vibration and noise are constant (Belda Hofheinz et al. 2024; Sams et al. 2022. Under these conditions, compactness, weight, and power autonomy become critical, as does the ability to rapidly interpret system data and alarms.
The Chilean cases demonstrated that the Lifemotion® ECMO system could be integrated into an air medical workflow without compromising operational safety or performance. Clinicians highlighted the advantages of a compact, lightweight configuration combined with battery-powered independence, allowing uninterrupted support during flight.
While airborne ECMO remains relatively uncommon globally, it represents an extreme stress test for portability (Belda Hofheinz et al. 2024; Sams et al. 2022). In regions where specialised ECMO care is concentrated in major urban centres, the ability to safely transport patients while maintaining extracorporeal support can directly influence access to advanced therapy.
Clinical Validation in European Reference Centres
Mobility and transport capability must be matched by performance in established ECMO centres. Germany has played a central role in Lifemotion’s early European clinical experience, with several university hospitals incorporating the system into both routine
and advanced care.
At the University Hospital of Hannover, clinicians conducted one of the first European cases using the system in April 2025. As an institution with extensive experience in advanced respiratory support, Hannover provided early insight into system behaviour under high-acuity conditions. Clinical teams reported effective gas exchange, a low pressure drop oxygenator, and a user interface that supported rapid orientation in time critical scenarios.
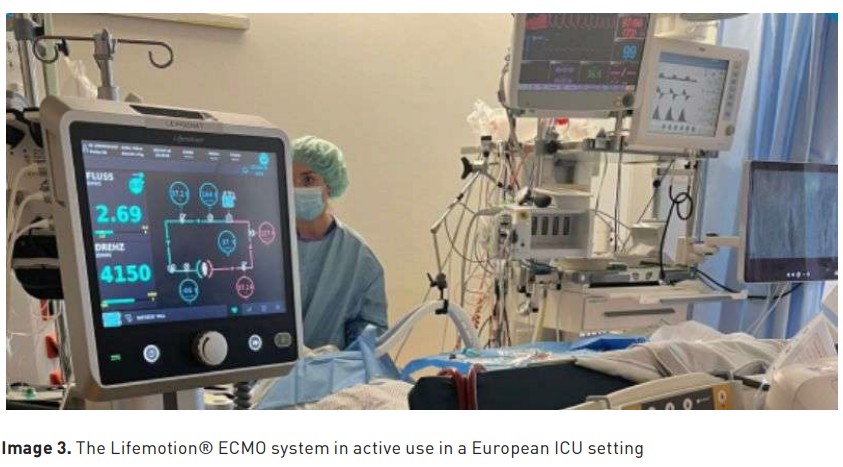
Further experience was reported at Universitätsmedizin Frankfurt, where the system was used across a spectrum of indications. An initial case in July 2025 involved a 78- year-old female patient supported for four days. Later in the year, a more complex case involved extracorporeal cardiopulmonary resuscitation and ECMELLA in a 66-year-old male patient, with five days of support.
Notably, the Frankfurt cases included multiple intra-hospital transports, offering additional validation of system stability during movement within the hospital environment. Clinical teams emphasised smooth workflow integration and consistent system performance across changing clinical contexts, with no reported technical complications.
Sustained Support and Surgical Integration
Taken together, these European cases demonstrate that performance expectations for the Lifemotion® system span the full spectrum of ECMO use, from acute transport and emergency deployment to complex surgical support and prolonged care. Yet clinical capability alone does not determine where ECMO can be delivered.
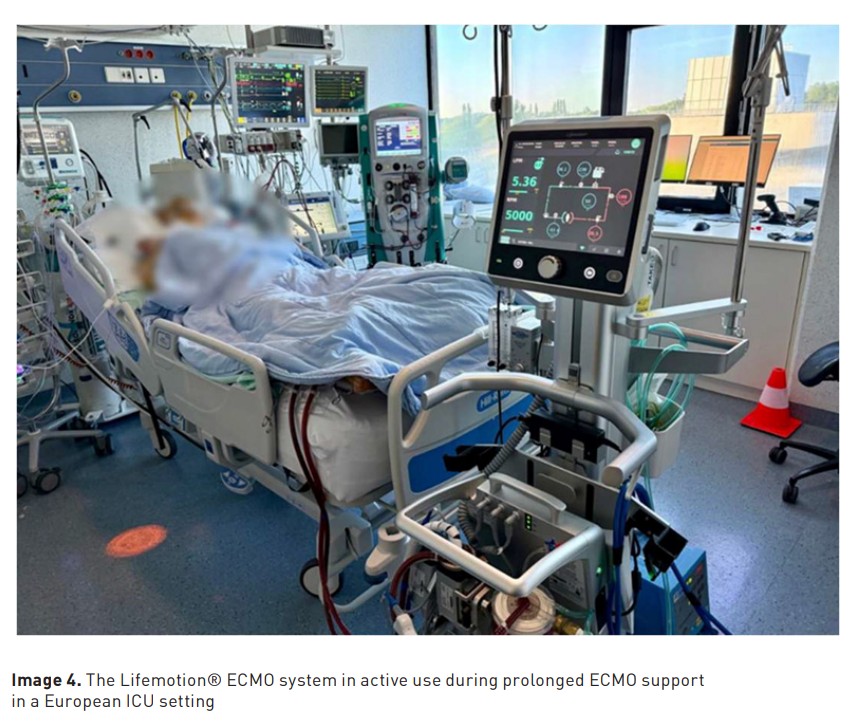
In Belgium, clinicians at one of the principal care centres for ECLS reported the first national case using the Lifemotion® ECMO system in June 2025. A 65-year-old male patient received 14 days of support following extracorporeal cardiopulmonary resuscitation, with successful weaning. Clinical teams described the system as intuitive for both experienced ECMO staff and newer team members, highlighting the importance of user-centric engineering in maintaining workflow efficiency over extended periods.
In Italy, a tertiary cardiac surgery centre reported a complex cardiac surgery case involving a 68-year-old male patient undergoing combined aortic valve replacement and mitral valve repair. Following emergency cardiopulmonary bypass, the patient required five days of VA-ECMO support due to severe pulmonary dysfunction and right ventricular overload.
Clinicians observed stable system performance throughout the support period and noted that the oxygenator remained free of visible clot formation despite the absence of systemic anticoagulation. While outcomes vary on a case-by-case basis, such observations are clinically relevant in high-risk surgical populations where bleeding risk and anticoagulation management must be carefully balanced.
Training and Capacity Building in South Africa
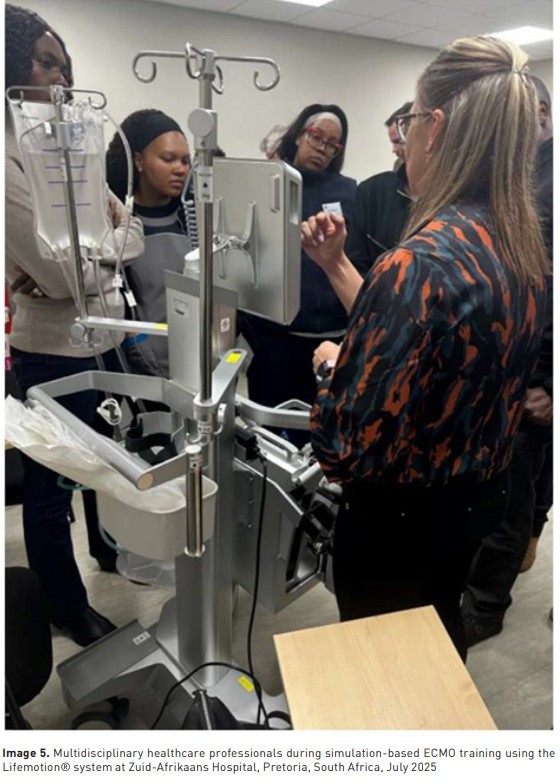
Technology adoption alone does not establish ECMO capability. In July 2025, Lifemotion participated in a two-day ECMO training programme at Zuid-Afrikaans Hospital in Pretoria, organised in partnership with Respiratory Care Africa and ECMO South Africa. The programme brought together multidisciplinary healthcare professionals for simulation-based training using the Lifemotion® ECMO system. Emphasis was placed on practical instruction, real-time decision making, and coordinated team response, reflecting best practices in ECMO education (Agerstrand et al. 2022; Halamek and Cady 2019).
Such initiatives highlight the role of system usability and integrated data visibility in training environments. Intuitive workflows and clear monitoring interfaces can support learning and reinforce safe practice, particularly in regions where ECMO programmes are still developing (Agerstrand et al. 2022; Halamek and Cady 2019).
Common Threads Across Early Clinical Experience
Taken together, early international clinical use of the Lifemotion® ECMO system reveals several consistent themes. Portability emerges not as an optional feature but as a foundational expectation, validated across ground transport, intra-hospital movement, and airborne deployment (Labib et al. 2022; Ozgur et al. 2025; Sams et al. 2022).
Battery-powered independence reduces reliance on fixed infrastructure and supports continuity of care during patient transfer. Equally important, safety features such as real-time monitoring and advanced alarm systems allow clinicians to maintain focus on patient management rather than device operation.
Finally, intelligent, user-centric system design appears to play an increasingly important role in workflow efficiency and clinical confidence, particularly in high-stress or unfamiliar environments.
Implications for the ECMO Market
The early international experience with the Lifemotion® ECMO system does not represent a reinvention of extracorporeal life support. Instead, it reflects an evolution in how such systems are expected to function within increasingly dynamic healthcare environments.
As care models become more distributed and patient pathways more fluid, ECMO platforms are being evaluated not only for clinical performance, but for their ability to support safe movement, rapid deployment, and continuity of care outside traditional ICU settings (Labib et al. 2022; Ozgur et al. 2025; Sams et al. 2022) Early clinical experience suggests that increased portability and system independence may help reduce geographic barriers to ECMO access, particularly in regions where specialised care is centralised, and patient transfer remains a limiting factor.
Regulatory approvals across Europe, the United Kingdom, Chile, South Africa, and Hong Kong further underscore the need for systems capable of meeting diverse operational and compliance requirements across healthcare systems with varying infrastructure and resources. For Lifemotion Medical Technology, a Chinese medical device company with more than a decade of experience in advanced life-support technologies, this multi-market approach reflects both the globalisation of critical care innovation and the increasing expectations for regulatory rigor across international healthcare systems.
From Spanish roadways to Chilean airspace, and from German university hospitals to South African training centres, these early experiences illustrate how expectations around ECMO are continuing to shift. In critical care, the ability to deliver life support where and when it is needed is becoming as consequential as the technology itself.
About Lifemotion®
Lifemotion® specialises in advanced Extracorporeal Membrane Oxygenation (ECMO) and Extracorporeal Life Support (ECLS) technologies, delivering critical care solutions for patients requiring advanced cardiopulmonary support. Headquartered in Shenzhen, China, with an international office in Mirandola, Italy — the world's leading medical technology hub — the company combines deep medical expertise with advanced manufacturing capabilities. Its vertically integrated approach ensures full control over production and supply chain security, from component manufacturing to final assembly. Committed to innovation and operational excellence, Lifemotion® delivers lifesaving ECMO solutions worldwide with uncompromising quality and reliability. For more information, visit www.lifemotionmedical.com
Disclaimer
Point-of-view articles are the sole opinion of the author(s) and are part of the ICU Management & Practice Corporate Engagement or Educational Community Programme.
All clinical details and feedback in this article are shared with permission and in accordance with the institutional publicity policies. No personal or patient-identifiable information is included. All photographs are published with the consent of the individuals depicted and in accordance with institutional image release policies. This content is intended for professional and informational purposes only and does not replace clinical guidelines, product labelling, or instructions for use. Device use should always follow CE-marked indications and local protocols.
References:
Agerstrand CL, Pruinelli L, Whelan L, Buber J, Biscotti M, Schiller RJ, et al. Development of a standardized assessment of simulation-based extracorporeal membrane oxygenation educational courses. ATS Sch. 2022;3(3):421–33.
Belda Hofheinz S, López Fernández E, García Torres E, Arias Dachary J, Boni L, Tajuelo Llopis I, et al. Primary neonatal and pediatric ECMO transport: First experience in Spain. Perfusion. 2024;39(3):623–32.
Halamek LP, Cady RAH, Sterling MR. Using briefing, simulation and debriefing to improve human and system performance. Semin Perinatol. 2019;43(8):151178.
Labib A, August E, Agerstrand C, Frenckner B, Laufenberg D, Lavandosky G, et al. Extracorporeal Life Support Organization guideline for transport and retrieval of adult and pediatric patients on ECMO support. ASAIO J. 2022;68(4):447–55.
Ozgur MM, Altinay E, Ogus H, Hancer H, Koksal HY, Yilmaz U, et al. Establishing an interhospital ECMO-transport program during a pandemic: Key lessons learned. Int J Artif Organs. 2025;48(1):40–7.
Sams VG, Anderson J, Hunninghake J, Gonzales M. Adult ECMO in the en route care environment: Overview and practical considerations of managing ECMO patients during transport. Curr Anesthesiol Rep. 2022;12(3):267–81.
