



ICU Management & Practice, Volume 26 – Issue 3, 2026
 PRINT OPTIMISED
SCREEN OPTIMISED
The primary barriers to the clinical adoption of cardiac output (CO) monitoring are the lack of access to and the high cost of monitoring tools. The ideal solution to improve accessibility might be a digital application (App) installed on standard multiparametric monitors, enabling instant activation of a top-tier pulse contour algorithm in patients with an arterial catheter. The App should also contain a visual decision support tool enabling clinicians to identify the underlying mechanisms of haemodynamic instability at a glance.
“Intervention should be based on the root cause of hemodynamic instability”. This statement is one of the recommendations of the Anesthesia Patient Safety Foundation (APSF) (Scott et al. 2024). The European Society of Anesthesiology and Intensive Care (ESAIC) published a similar statement on haemodynamic monitoring and management (Saugel et al. 2025). They recommend that the “treatment of hypotension be based on underlying causes, which include vasodilation, hypovolaemia, bradycardia, and cardiac dysfunction”. While heart rate is continuously monitored in all surgical patients, making bradycardia easy to detect, distinguishing between vasodilation, hypovolaemia, and cardiac dysfunction may be challenging. However, once cardiac output (CO) is monitored, the picture becomes clear. Indeed, low blood pressure with preserved blood flow (normal or high CO) is explained by vasodilation. In contrast, low blood pressure with low blood flow is frequently related to hypovolaemia, though it may occasionally reflect cardiac dysfunction. To discriminate between these two scenarios, clinicians can quantify changes in CO during a fluid bolus (or a passive leg raise manoeuvre). This approach allows clinicians to identify fluid-responders and non-responders. When blood pressure and CO are low, and patients do not respond to a fluid challenge, cardiac dysfunction is suspected. In summary, monitoring CO enables clinicians to easily and quickly identify the root cause of hypotension and tailor treatment accordingly (Michard et al. 2025a). In this respect, the ESAIC suggested “monitoring cardiac output in patients with high baseline risk for complications or in patients having high-risk surgery” (Saugel et al. 2025).
Underuse of CO Monitoring in High-Risk Surgical Patients
Surveys and observational studies have shown that cardiac output (CO) monitoring is underused in high-risk surgical patients. An observational study conducted in 23 University Hospitals in France found that only 10% of patients at high risk of postoperative complications had their CO monitored during the surgical procedure (Molliex et al. 2019). Another large observational study using data from 28 European nations reported a similar proportion of patients with CO monitored during major surgery (Ahmad et al. 2015). This highlights a significant gap between current guidelines and real-life practice: Although CO monitoring is recommended for high-risk surgical patients, only one in ten actually receives it.
It is important to understand why anaesthesiologists do not routinely monitor CO in high-risk surgical patients. A survey published a couple of years ago among ESAIC members suggested that the primary barriers to the clinical adoption of CO monitoring were the lack of access to and the high cost of monitoring tools (Flick et al. 2023). In another recent worldwide survey, 72% of respondents said they would use CO monitoring tools more often if they were less expensive (Michard et al. 2025b). As a matter of fact, CO monitoring can be expensive. Beyond the fixed cost of the dedicated haemodynamic monitor (which can exceed €50k), ongoing expenses include dedicated consumable pressure sensors, which typically cost between €100 and €400 per unit. We estimated that, given the current adoption rate in France, this already represents about €67 million per year (Michard et al. 2023). To put this into perspective, this amount could cover the salaries of > 2000 nurses each year in France or fund the purchase of >10,000 pocket echo devices. We also estimated that if ESAIC guidelines were followed, the cost of these consumable pressure sensors would quickly reach €1 billion per year in Europe (Michard et al. 2024). Therefore, solutions to make CO monitoring more accessible are needed. Of note, all these considerations also apply to ICUs where most patients with circulatory shock are monitored with an arterial catheter, but only a small proportion have their CO monitored (Boulain et al. 2015).
Improving Access to CO Monitoring
The first solution to increase access to CO monitoring is to prioritise pulse contour algorithms that analyse blood pressure waveforms recorded with a standard pressure transducer: the low-cost transducer clinicians already use to continuously monitor blood pressure in patients with an arterial catheter (most high-risk patients have one). This would eliminate the need for specialised pressure transducers that cost up to €400/unit. Interestingly, using standard rather than specialised transducers is associated with a significant decrease in plastic waste (Michard et al. 2023). This is why pulse contour algorithms compatible with standard transducers are now often referred to as “green” algorithms (Michard et al. 2024). A second approach to improve access to CO monitoring is to integrate one of these algorithms into standard multiparametric monitors, which are currently used to record vital signs. This would eliminate the need for both specialised expensive pressure transducers and the dedicated haemodynamic monitor (Michard et al. 2025a). This would further decrease the cost and carbon footprint of CO monitoring. It would also make CO monitoring available on demand and instantly, with a simple tap on the screen of any monitor installed in operating rooms and ICUs.
All pulse contour algorithms are not created equal. Most are highly sensitive to vascular tone and underestimate CO in patients with vasodilation (Metzelner et al. 2012), a concern when patients receive anaesthetic drugs or have sepsis. The accuracy of the Pressure Recording Analytical Method (PRAM) algorithm is less influenced by vascular tone (Franchi et al. 2012). In several clinical studies, PRAM measurements were interchangeable (percentage error < 30%) with those obtained from reference methods, namely pulmonary thermodilution, transpulmonary thermodilution, and echocardiography-Doppler. In two recent meta-analyses comparing the performance of existing pulse contour algorithms, PRAM had the best precision (lower percentage error) and the best trending ability (highest concordance rate) (Barrachina et al. 2026; Flick et al. 2026). PRAM offers the additional advantage of including a filter able to detect and correct underdamping phenomena. Originally part of a stand-alone CO monitor, it has since been integrated into a standard bedside monitor.
Visual Decision Support
Traditionally, haemodynamic variables are presented as separate metrics in tabular form, offering little emphasis on their physiological relationships or clinical significance. This forces clinicians to synthesise the data mentally, a process that can be time-consuming and error-prone. The human brain processes visual information significantly faster than text. Visual tools leverage clinicians' innate ability to process graphical information rapidly, improving understanding of cardiovascular physiology and enabling recognition of haemodynamic profiles at a glance (Michard and Abou-Arab 2026). Multiple studies have shown that graphical displays improve the detection of acute changes in patient physiologic status during anaesthesia administration and reduce the time to detection and treatment of cardiopulmonary adverse events. Studies have also shown that anaesthesiologists using graphical displays make significantly fewer diagnostic errors when interpreting physiologic data.
Describing haemodynamic phenotypes plays a key role in educating healthcare professionals about cardiovascular physiology, enhancing understanding of shock mechanisms, and informing treatment strategies. Haemodynamic monitors have increasingly incorporated cockpit-style displays featuring colour-coded dials to flag deviations from normal ranges or therapeutic targets. A logical next step is to organise these visualisations around physiological interdependencies (Michard and Abou-Arab 2026). For example, mean arterial pressure results from CO and systemic vascular resistance; CO, in turn, depends on stroke volume and heart rate. Additionally, since most anaesthetic agents reduce vascular tone, depth of anaesthesia plays a critical role in determining systemic vascular resistance. Visualising these relationships could allow clinicians to instantly recognise haemodynamic profiles, facilitating timely and accurate interventions (Figure 1).
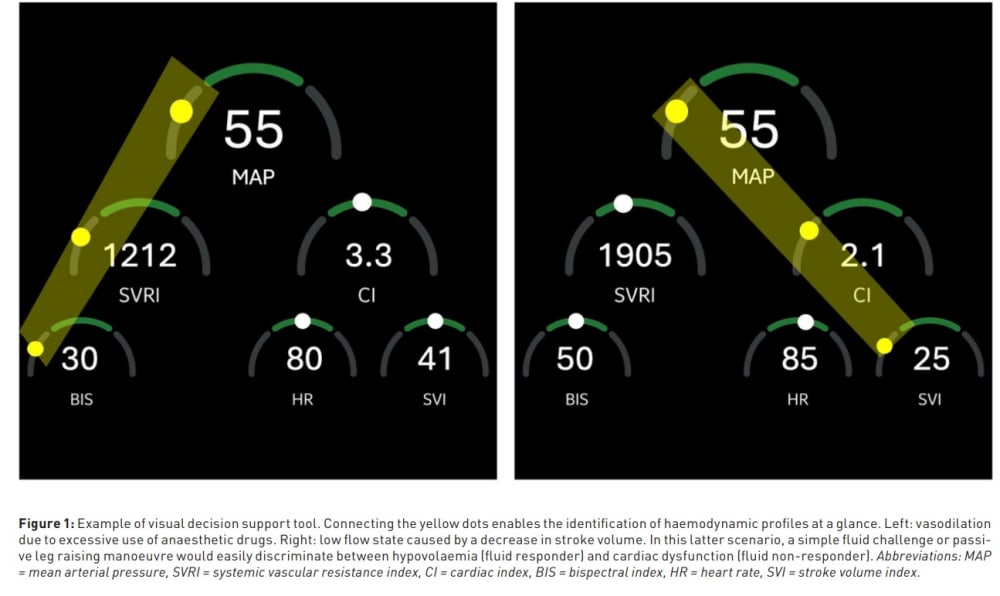 Rethinking CO Monitoring
In summary, the ideal CO monitoring solution might be a digital application (App) installed on standard multiparametric monitors, enabling instant activation of CO monitoring in patients with an arterial catheter already in place. The App should be activable on demand, at any time, and at a low cost/patient. It should contain a top-tier green pulse contour algorithm, not influenced by vascular tone and validated against reference methods. The App should also contain a visual decision support tool enabling clinicians to identify the underlying mechanisms of haemodynamic instability at a glance. The combination of these features would make CO monitoring easy (Figure 2), ensure more clinicians can follow current guidelines, and more patients can benefit from personalised haemodynamic care. This evolution would be aligned with the concept of techquity, which consists of improving equity with smart and affordable technological innovations.

Conflict of Interest
FM is the founder and managing director of MiCo, a Swiss consulting and research firm. MiCo does not sell any medical devices. KL received consulting fees from Philips and lecturing/education fees from Vygon.
References:
Ahmad T, Beilstein CM, Aldecoa C, et al. Variation in haemodynamic monitoring for major surgery in European nations: secondary analysis of the EuSOS dataset. Perioper Med (Lond). 2015;4:8.
Barrachina B, Vinuesa C, Iriarte I, et al. Trending ability and accuracy of minimally invasive pulse wave analysis devices: a systematic review and meta-analysis. Anesth Analg. 2026. Epub ahead of print.
Boulain T, Boisrame-Helms J, Ehrmann H, et al. Volume expansion in the first 4 days of shock: a prospective multicenter study in 19 French intensive care units. Intensive Care Med. 2015;41:248-256.
Flick M, Joosten A, Scheeren T, et al. Haemodynamic monitoring and management in patients having non-cardiac surgery. A survey among members of the European Society of Anaesthesia and Intensive Care. Eur J Anaesthesiol Intensive Care. 2023;2:e0017.
Flick M, Muller DX, Bergholz A, et al. Agreement of minimally invasive pulse wave analysis with pulmonary artery and transpulmonary thermodilution cardiac output measurements in perioperative and intensive care medicine: a systematic review and meta-analysis. Br J Anaesth. 2026. Epub ahead of print.
Franchi F, Silvestri R, Cubattoli L, et al. Comparison between an uncalibrated pulse contour method and thermodilution technique for cardiac output estimation in septic patients. Br J Anaesth. 2011;107:202-208.
Metzelder S, Coburn M, Fries M, et al. Performance of cardiac output measurement derived from arterial pressure waveform analysis in patients requiring high-dose vasopressor therapy. Br J Anaesth. 2011;106:776-784.
Michard F, Futier E, Desebbe O, et al. Pulse contour techniques for perioperative hemodynamic monitoring: a nationwide carbon footprint and cost estimation. Anaesth Crit Care Pain Med. 2023;42:101239.
Michard F, Romagnoli S, Saugel B. Make my haemodynamic monitor GREEN: sustainable monitoring solutions. Br J Anaesth. 2024;133:1367-1370.
Michard F, Chew M, Futier E. Perioperative cardiac output monitoring for the many. Intensive Care Med. 2025;51:1526-1529.
Michard F, Divatia J, Nacul FE, et al. Access to haemodynamic evaluation tools in middle-income countries: a survey of 1593 anaesthetists and intensivists from 39 nations. BJA Open. 2025;17:100515.
Michard F, Abou-Arab O. Hemodynamic phenotyping 4.0. Anaesth Crit Care Pain Med. 2026;45:101647.
Molliex S, Passot S, Morel J, et al. A multicentre observational study on management of general anaesthesia in elderly patients at high-risk of postoperative adverse outcomes. Anaesth Crit Care Pain Med. 2019;38:15-23.
Saugel B, Buhre W, Chew MS, et al. Intra-operative haemodynamic monitoring and management of adults having noncardiac surgery: a statement from the European Society of Anaesthesiology and Intensive Care. Eur J Anaesthesiol. 2025;42:543-556.
Scott MJ; APSF Hemodynamic Instability Writing Group. Perioperative patients with hemodynamic instability: consensus recommendations of the Anesthesia Patient Safety Foundation. Anesth Analg. 2024;138:713-724.



